
Limited-benefit coverage, not major medical insurance
Critical illness and cancer insurance
Critical illness coverage may pay a policy-defined lump sum after a covered diagnosis. It is designed to supplement—not replace—comprehensive health insurance.
Who it’s designed for
- People with a high-deductible health plan or a large Medicare Advantage out-of-pocket maximum
- People who couldn’t absorb several thousand dollars of unexpected cost without borrowing
- Working people whose income would stop during recovery
- People with family history of heart disease or stroke
- People who want one policy covering several conditions rather than a cancer-only plan
What it generally covers — and generally doesn’t
Generally covered
- Heart attack, stroke, and coronary artery bypass surgery
- Invasive cancer, end-stage renal failure, and major organ transplant
- On many policies: paralysis, ALS, severe burns, or blindness
- A lump sum paid to you, on top of Medicare or any health plan
- Sometimes a partial benefit for a lesser event, such as an angioplasty or in-situ cancer
Generally not covered
- Conditions not named in the policy — the list is exhaustive, not illustrative
- An event that doesn’t meet the contract’s clinical definition, even if your doctor uses the same word
- Diagnoses inside the waiting period, or tied to a pre-existing condition
- Medical bills as such — this pays a fixed sum, not a percentage of charges
- A second claim for the same condition, unless a recurrence benefit is included
Eligibility & enrollment considerations
Health questions, and age bands
Premiums rise with age and issue ages are capped, often in the seventies. A prior heart attack, stroke or cancer usually rules out that condition or the whole policy.
Choose the benefit amount
Typically $5,000 to $50,000. A sensible anchor is your health plan’s out-of-pocket maximum plus a few months of expenses.
Apply any time
Not tied to Medicare enrollment periods. Coverage typically begins the first of the month after approval.
Read the definitions with us
The covered-condition definitions are the whole product. We’ll go through them line by line before you sign, not after a claim.
Important critical illness insurance limitations
- Payment depends on meeting a clinical definition. A “mild” heart attack may not qualify under some contracts.
- Benefits may reduce at a certain age, often 65 or 70, on some policies.
- Waiting periods and pre-existing condition provisions apply at the start.
- Coverage usually pays once per condition and has a lifetime maximum across all conditions.
- It is not health insurance, not disability income, and not a substitute for either.
Frequently asked questions
Do I still need this if I have a Medigap plan?
Often not. A good Medigap policy already removes most of the medical exposure a critical illness policy is meant to cushion. Where it still helps is non-medical cost — travel, a caregiver, lost income.
Is the payout taxable?
Benefits on a policy you paid for with after-tax dollars are generally not taxable income, but tax treatment depends on your situation. Ask your tax preparer — we’re not tax advisors.
What if I never get sick?
Then you’ve paid premiums for protection you didn’t need, like any insurance. A few policies offer a return-of-premium rider at extra cost; whether that’s worth it is arithmetic we can run.
Official resource
Critical illness insurance next to the products it is confused with
Four products get sold as though they were interchangeable. They are not, and choosing between them starts with naming the loss you are actually worried about.
Critical illness insurance pays a lump sum on a covered diagnosis, once the definition is met. It does not care whether you stopped working or how long you were in hospital.
Disability income insurance replaces a portion of earnings while you cannot work, month by month, for as long as the definition of disability continues to be met. It is the better answer if the fear is a lost salary rather than a lump of immediate costs, and it is the harder of the two to buy after 60.
Hospital indemnity cover pays a fixed amount per day, or per admission, whether or not a listed diagnosis applies. It suits someone whose exposure is the daily copay on an inpatient stay, which is a common gap on Medicare Advantage plans.
Accident cover pays on injury rather than illness, and pays nothing at all for the diagnoses critical illness insurance is bought for.
Households sometimes hold two of these without realizing the overlap, and more often hold the one that does not answer their actual worry. Write the worry down first, in a sentence, and the product usually chooses itself.
Sizing critical illness insurance against the gap it is meant to fill
A benefit chosen because it sounded like a reassuring number is a benefit chosen badly. Work out the hole first.
Start with your health plan’s out-of-pocket maximum, because that is the ceiling on covered, in-network care in a bad year. For an ACA-compliant plan in 2026 the legal maximum is $10,600 for one person and $21,200 for a family, and most plans sit below that. On a Medicare Advantage plan the 2026 in-network cap is $9,250, with combined in and out-of-network exposure on a PPO reaching $13,900.
If you are on Original Medicare without a supplement, there is no annual cap at all. That absence is the single strongest argument for holding something that pays cash, and it is also an argument for looking at a supplement first.
Then add what insurance of any kind does not pay. Travel to a treatment center and somewhere to stay. Time off work for the person driving you. Childcare or eldercare that was being done for free. Home adjustments after surgery. Higher heating bills and easier food during months of treatment. The deductible resetting if the illness spans a calendar year end.
That total is what critical illness insurance is sized against. It is usually larger than the medical bills and smaller than the round number in an advertisement.
Cover through work, and whether it comes with you
Critical illness insurance offered at work is usually cheap, often issued with few or no health questions, and rarely large. For someone with a health history that would complicate an individual application, that guaranteed acceptance is genuinely valuable and worth taking.
Two questions decide whether it is enough. Ask whether the benefit reduces at a stated age, because many group schemes halve it at 65 or 70 — precisely when the diagnoses become more likely. And ask whether the cover is portable if you leave, at what price, and within what window, because the answer is frequently no.
Where the workplace policy is small and not portable, an individual policy underneath it does the job the group scheme cannot, and it does not disappear when the job does.
How the money is generally treated for tax
The usual position is that benefits from a policy you paid for yourself, with money that had already been taxed, are received free of income tax. Where an employer paid the premium and did not include it in your income, the benefit may be taxable instead.
Paying for a workplace policy through a pre-tax payroll arrangement can therefore change the answer, which is worth knowing before you choose that option rather than after a claim.
We are insurance agents rather than tax advisers, and this is a point where the detail depends on your own circumstances and your state. Ask whoever prepares your return, and ask before you enroll, because the enrollment choice is the part that is hard to undo.
One last thing worth checking on any critical illness insurance policy, group or individual: whether a benefit already paid reduces the death benefit of a life policy attached to it. On combined products it often does, and nobody volunteers that at the point of sale.
If you already hold cover of this kind, find the certificate in the drawer where it has been sitting and read the schedule of covered conditions before you renew it. Most people who own critical illness insurance have never read that page, and it is the page a claim will turn on. We will go through it with you at no charge, whether or not the policy came from us.
Check the source, then ask for personal help
Educational information is general. A licensed agent can help with plan comparisons; agents do not provide medical, legal, or official eligibility advice.
How critical illness insurance actually pays out
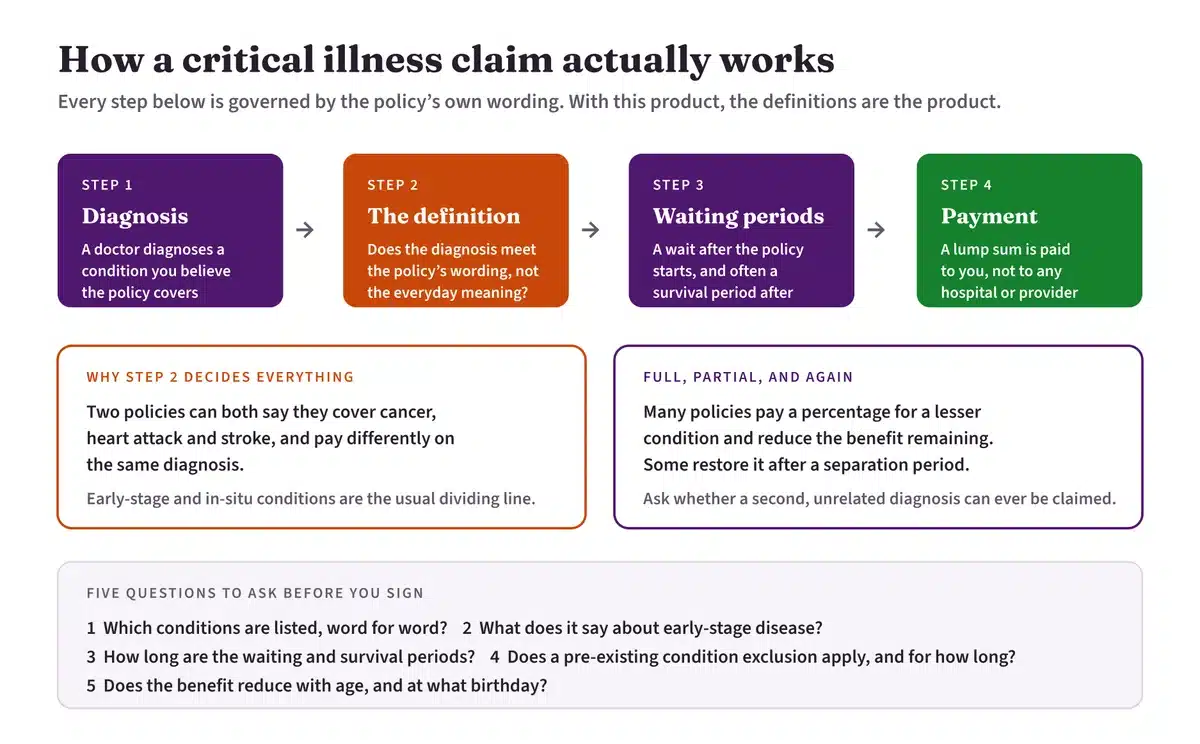
Critical illness insurance pays a single lump sum in cash when you are diagnosed with one of the conditions the policy names, provided the diagnosis meets the definition written into the contract.
The money is yours. It is not paid to a hospital, it is not reduced by what your health plan paid, and there is no requirement to spend it on treatment. In practice people use it for the things health insurance never touches: the mortgage during months off work, travel and lodging near a specialist center, home adaptations, childcare, or replacing a spouse’s income while they take time off to help.
Because it pays on diagnosis rather than on bills, critical illness insurance arrives early — often within weeks — which is precisely when a household’s costs spike and its income falls.
With critical illness insurance, the definitions are the product
This is the part that decides whether a claim is paid, and the part most buyers skip.
A policy does not cover “cancer”. It covers cancer as the contract defines it, and definitions vary between carriers in ways that matter enormously. Many policies exclude or heavily reduce payment for early-stage and in-situ cancers, and for non-melanoma skin cancers.
“Heart attack” usually requires specific diagnostic evidence — troponin markers, ECG changes — rather than a doctor’s general description. Angina is normally excluded. “Stroke” typically requires neurological deficit persisting beyond a stated period, which is why transient ischaemic attacks are usually excluded.
Read the condition list and the definitions with someone before you buy. We will go through them line by line with you; it is the single most useful hour you can spend on critical illness insurance.
What critical illness insurance typically covers
Most policies build outward from three core conditions: cancer, heart attack and stroke. Those three account for the overwhelming majority of paid claims.
Broader policies add coronary artery bypass surgery, major organ transplant, end-stage renal failure, paralysis, coma, severe burns, and sometimes conditions such as multiple sclerosis, Parkinson’s or ALS.
More conditions is not automatically better. A long list padded with rare diagnoses at reduced payout percentages can cost more than a short list that pays the full benefit on the three things most likely to happen. Compare what each condition actually pays, not how many are named.
Partial payments and recurrence in critical illness insurance
Many conditions pay a percentage rather than the full benefit — an early-stage cancer might pay 25%, an angioplasty 10%. Ask for the schedule of percentages, not just the headline benefit amount.
Ask too whether the benefit is reduced or exhausted after a first claim. Some critical illness insurance policies terminate once the full benefit is paid; others restore cover for unrelated conditions after a separation period, commonly six or twelve months.
And ask whether a recurrence of the same condition can be claimed again after a defined interval. For cancer in particular this is a meaningful difference between products.
Who critical illness insurance suits

It suits people whose household would face a cash-flow problem, not just a medical bill, if they were seriously ill. If a diagnosis would mean months of reduced income while fixed costs continued, that gap is what this product is for.
It suits people with high-deductible health cover, and people on Medicare Advantage plans facing an annual out-of-pocket maximum they would struggle to absorb.
It is worth less to someone with substantial liquid savings, or with a comprehensive Medigap policy and a stable retirement income, because the gap it fills is already covered.
And it is not a substitute for health insurance, disability cover or long-term care insurance. Those are different problems with different products.
Critical illness insurance underwriting and waiting periods
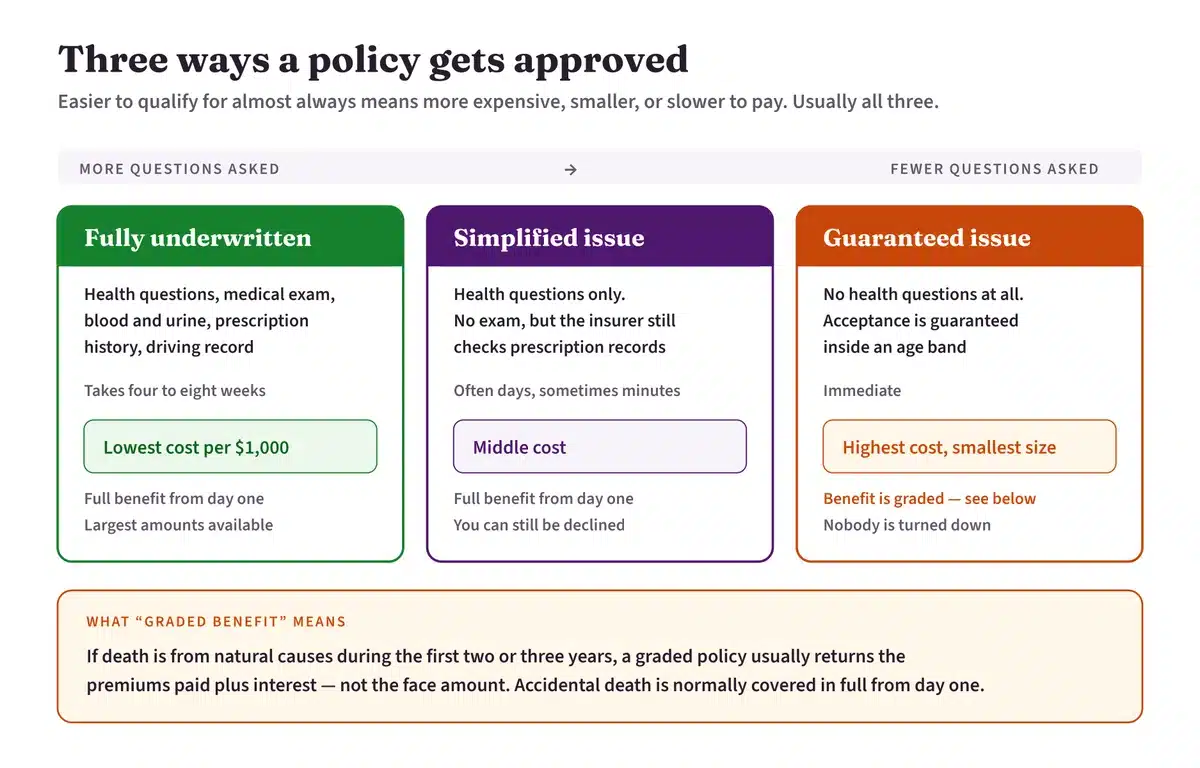
Critical illness insurance is medically underwritten. Expect health questions, a prescription-history check, and for larger benefit amounts sometimes an exam. A personal history of the covered conditions usually rules out cover for those conditions and may rule out the policy.
Almost every policy carries a waiting period at the start — commonly 30 to 90 days — during which a diagnosis is not covered. Pre-existing condition look-backs apply as well, typically over the twelve months before issue.
Rates are generally set by age band and can rise as you move between bands, so check whether the premium you are quoted is level or age-banded before you compare it with anything else.
Common mistakes with critical illness insurance
Buying on the number of conditions. Buy on the definitions and the payout percentages.
Assuming any cancer diagnosis pays in full. Early-stage and in-situ diagnoses very often do not.
Overlooking the waiting period. A diagnosis in month one is usually not covered.
Treating it as disability cover. It pays on diagnosis, not on inability to work, and it pays once rather than monthly.
Not telling your family it exists. Benefits go unclaimed for this reason more often than you would think.
Check any of this independently
- NAIC consumer tools — agent license and carrier complaint records
- Medicare.gov — Medicare costs — what your existing cover already absorbs
- SHIP National Technical Assistance Center — free counseling in your state
- American Cancer Society — independent information on staging and treatment
- Critical illness insurance next to the products it is confused with
- Sizing critical illness insurance against the gap it is meant to fill
- Cover through work, and whether it comes with you
- How the money is generally treated for tax
Related guides on this site
- Hospital indemnity cover — a daily cash benefit rather than a lump sum
- What Medicare Advantage costs — the out-of-pocket maximum this is meant to cushion
- How Medigap works — the alternative way to close the same gap
- Book a no-cost appointment
Or call (877) 808-2900. We will read the condition definitions with you before you apply, and we will tell you when critical illness insurance is not worth buying in your situation.
Personal guidance · No additional fee