
Fixed benefits for covered hospital events
Hospital indemnity insurance
Hospital indemnity insurance may pay fixed cash benefits for covered admissions or days in a hospital. It supplements primary medical coverage and is not a substitute for it.
Who it’s designed for
- Medicare Advantage members whose plan charges a daily inpatient copay for the first several days — this is the classic pairing
- People on Original Medicare without Medigap, facing the Part A deductible each benefit period
- People with a condition likely to lead to admissions or a skilled nursing stay
- People who want a cash cushion for the incidentals of a hospital stay: parking, meals, a family member’s travel
What it generally covers — and generally doesn’t
Generally covered
- A fixed daily cash benefit for covered inpatient hospital days, up to a stated number of days
- Optional riders: skilled nursing facility days, ambulance, outpatient surgery, observation stays, emergency room visits
- Money paid to you regardless of what Medicare or your plan pays the hospital
- Benefits usable for anything — the plan’s copay, a bill at home, a caregiver
Generally not covered
- Days beyond the policy’s maximum per stay or per year
- Observation status that isn’t a formal inpatient admission, unless a rider covers it
- Admissions inside the waiting period or tied to a pre-existing condition
- Doctor bills, drugs and outpatient care — this pays per day, not per service
- Long-term custodial or nursing home care
Observation vs. admitted — the trap worth knowing
You can spend two nights in a hospital bed and still be classified as an outpatient under “observation status.” That classification changes how Medicare pays and can void a benefit that requires formal inpatient admission. Ask whether a policy covers observation stays; ask the hospital which status you’re in.
Eligibility & enrollment considerations
Match it to your plan’s copay
If your Medicare Advantage plan charges, say, a daily copay for the first five days, a benefit sized to that is the point of the policy. We read your plan’s Summary of Benefits first.
Health questions apply
Underwriting is usually a short list of questions. Recent admissions or pending procedures can cause a decline.
Any month of the year
Independent of Medicare’s enrollment calendar. Many people add it right after choosing a Medicare Advantage plan in the fall.
Not needed with most Medigap plans
If a Medigap policy already covers your Part A deductible and hospital coinsurance, this is usually duplicate coverage. We’ll say so rather than sell it.
Important limitations
- Day limits are the main constraint. A long stay can exhaust the benefit well before discharge.
- The benefit is a fixed dollar amount and does not rise with the hospital’s charges.
- Pre-existing condition provisions commonly apply for six to twelve months after issue.
- Riders — ambulance, skilled nursing, observation — each add premium; buy the ones that match your actual risk.
- This is supplemental coverage. It never replaces Medicare, Medigap or a Medicare Advantage plan.
Frequently asked questions
Is this the same as Medigap?
No. Medigap pays a share of Medicare-approved charges and only works with Original Medicare. Hospital indemnity pays you a flat daily amount and works alongside a Medicare Advantage plan, which Medigap cannot.
How do I claim?
You submit the admission and discharge documentation to the carrier and they pay you directly. Call us and we’ll help with the paperwork — that’s part of the service.
Does it cover a nursing home?
Only skilled nursing days following a qualifying hospital stay, and only if the policy includes that rider. Long-term custodial care is a different product entirely.
Official resource
Observation status is the reason this product exists, and almost nobody explains it
You can spend three nights in a hospital bed, be seen by hospital doctors, eat hospital food, and never be admitted. That is observation status, and it is an outpatient category despite everything about it looking like an admission.
It matters for two reasons. Under Original Medicare, an observation stay is billed under Part B rather than Part A, so instead of one inpatient deductible you face outpatient coinsurance on each service, and self-administered drugs given during the stay are often not covered at all.
The second reason is worse. Medicare only covers skilled nursing facility care after a qualifying inpatient stay of at least three consecutive days, and observation days do not count toward it. People are discharged to a nursing facility believing it is covered, and discover it is not.
Hospitals must give you a written notice when you have been under observation for more than 24 hours, explaining your status and what it means. Read it rather than filing it, and ask whether the status can be reviewed while you are still there, because it is far harder to change afterwards.
This is where hospital indemnity insurance behaves differently from everything else. It pays on the event described in the policy, not on how Medicare classified the stay — but only if the policy is written to include observation days. Some are. Many are not, and pay only on formal inpatient admission.
That single clause is the most important thing in the contract. Ask it directly: does this policy pay for observation stays, or only for inpatient admissions?
How the benefit is actually structured
Hospital indemnity insurance pays a fixed sum on a defined event. The bill is irrelevant to it, and the money comes to you rather than to the hospital.
Beyond that, the structures vary more than the marketing suggests, and four questions separate them.
Per day or per admission? A per-day benefit pays for each day of a stay. A per-admission benefit pays once, however long you are there. The two are not comparable on headline figures alone.
How many days, and is the first one different? Many policies pay a higher amount for the first day and less thereafter, and most cap the number of days per stay or per year.
Is there a limit on separate stays? Policies commonly require a gap between admissions before a second one counts as a new stay rather than a continuation.
What else does it pay for? Riders for ambulance transport, emergency room visits, outpatient surgery, intensive care and skilled nursing are common. Each has its own limits.
Where it fits, and where it does not
The clearest case is somebody on a Medicare Advantage plan with a daily inpatient copay. Those copays typically run for the first several days of a stay and can add up quickly, and a per-day hospital indemnity benefit is designed to sit exactly there.
It fits less well alongside a comprehensive Medicare Supplement, because Plan G already covers the Part A deductible and inpatient coinsurance. Buying both is not wrong, but the overlap should be a decision rather than an accident.
And it is never a substitute for comprehensive coverage. Hospital indemnity insurance pays a fixed sum and stops; it will not absorb a six-figure hospital bill. Anyone selling it as an alternative to a health plan or to Medicare itself is misleading you.
Two last details worth confirming before you sign. Whether a pre-existing condition exclusion applies and for how long, since these policies commonly carry one of six or twelve months. And whether the benefit reduces at a stated age, because several do at 65 or 70.
Benefits from a policy you paid for yourself with money already taxed are generally received free of income tax. Where an employer paid the premium, the answer can differ. That is a question for whoever prepares your return rather than for an agent, and it is worth asking before you enroll rather than after a claim.
None of this is a reason to dismiss hospital indemnity insurance out of hand. It is a reason to read the schedule of benefits rather than the brochure, and to buy it for a gap you have actually identified rather than for a worry in general.
Bring your current plan’s summary of benefits when you compare. If it shows a daily inpatient copay, that number is what any hospital indemnity insurance policy should be sized against, and the arithmetic takes about five minutes.
Ask for the outline of coverage and read the exclusions before you sign anything. On a hospital indemnity insurance policy the exclusions and the waiting period are where the product actually lives.
Check the source, then ask for personal help
Educational information is general. A licensed agent can help with plan comparisons; agents do not provide medical, legal, or official eligibility advice.
How hospital indemnity insurance actually pays you
Hospital indemnity insurance pays you a fixed cash amount when a covered event happens. It does not pay the hospital, it does not coordinate with your health plan, and it does not care what the hospital charged.
That is the whole mechanism, and it is why the product is easy to misunderstand. A policy that pays a set amount per day of inpatient admission pays that amount whether the bill was two thousand dollars or twenty. The money arrives in your bank account and you decide what it is for — the plan’s copay, the mortgage, the drive to and from the hospital, or the wages a spouse gave up to be there.
Because the benefit is cash to you, hospital indemnity insurance stacks on top of Medicare, on top of a Medicare Advantage plan, and on top of employer cover. Nothing is offset.
Why it exists mainly for Medicare Advantage members
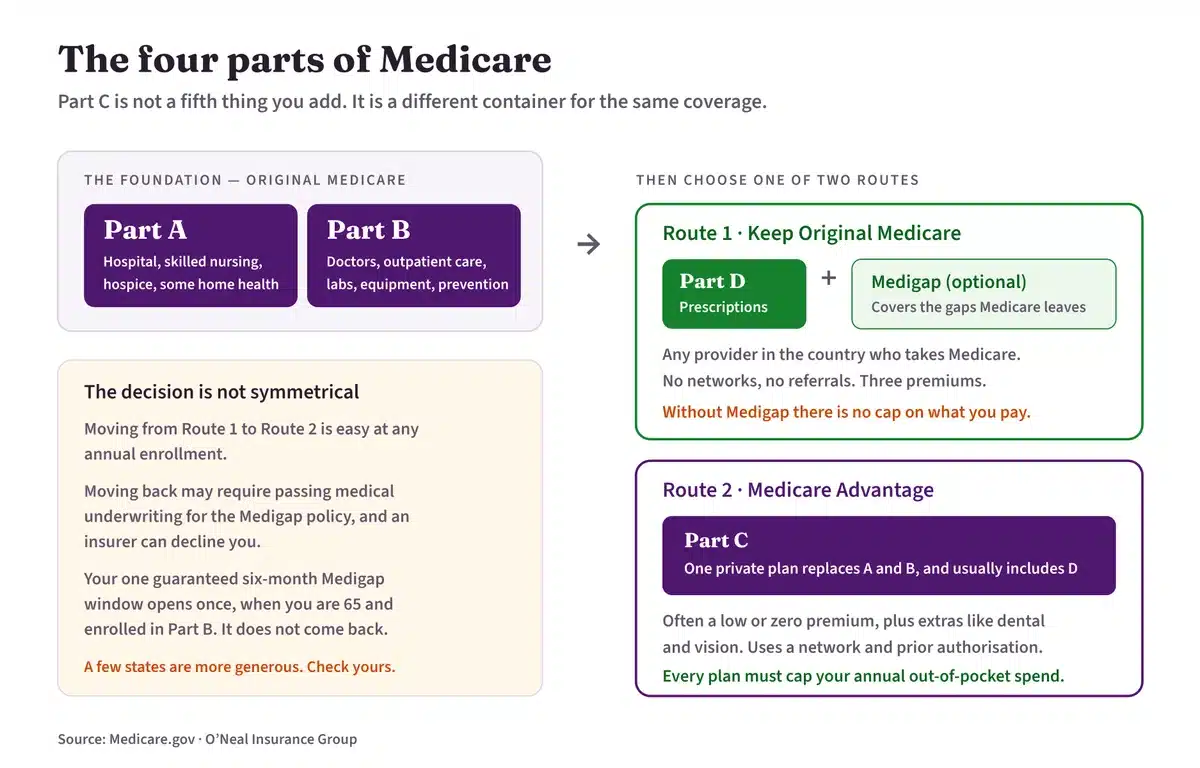
Original Medicare charges a single Part A deductible per benefit period for an inpatient stay. Most Medicare Advantage plans work differently: they charge a daily copay for the first several days of an admission, and those daily amounts add up quickly.
Hospital indemnity insurance is built to sit against exactly that. The usual approach is to match the benefit period to the number of copay days in your plan — if your plan charges a copay for the first six days, a policy paying for six days lines up with the exposure.
This is why the product is worth much less to someone holding a Medigap Plan G or Plan N. Those plans already cover the Part A deductible, so there is little left for the cash to do. If an agent recommends hospital indemnity insurance alongside a comprehensive Medigap policy, ask them to explain precisely what gap it fills.
Observation status: the hospital indemnity insurance trap
A hospital can keep you in a bed, on a ward, overnight or longer, and still classify you as an outpatient under observation rather than admitting you.
That distinction has real consequences. Observation is billed under Part B rather than Part A, and it does not count toward the three-day inpatient stay Medicare generally requires before it will cover skilled nursing care afterwards.
It matters for this product too, because many hospital indemnity insurance policies pay only on inpatient admission. Some include an observation benefit; many do not. Ask the question directly and get the answer in the policy language, not from a brochure.
Separately, hospitals are required to give Medicare patients written notice when they are receiving observation services rather than being admitted. If you are ever handed that notice, keep it — and ask the hospital whether admission is being considered.
Hospital indemnity insurance riders, and what they are worth
Most hospital indemnity insurance is sold as a base inpatient benefit with optional riders attached. Common ones include ambulance transport, emergency room visits, outpatient surgery, skilled nursing facility stays, cancer or heart attack lump sums, and intensive care at an enhanced daily rate.
Riders are where the premium goes up fastest, so buy the ones matched to a real exposure in your own plan. If your Medicare Advantage plan already has a low ambulance copay, an ambulance rider is buying something you have.
The skilled nursing rider is the one most often underrated. A stay in a skilled nursing facility after a hospital admission carries daily copays on most Advantage plans from around day twenty-one, and that is a longer and larger exposure than the hospital stay that preceded it.
Health questions and waiting periods on hospital indemnity insurance
Hospital indemnity insurance is medically underwritten with health questions. There is no exam, but the questions are real and answering them inaccurately puts a future claim at risk.
Most policies carry a pre-existing condition limitation — commonly a look-back at the six or twelve months before the policy started, with a matching period during which claims arising from those conditions are not paid. Read that clause before you buy, because it is the clause claims are most often denied under.
You can apply in any month of the year. This is not a Medicare product, so it is not tied to Annual Enrollment, and there is no penalty for buying it later. The only thing that changes with time is your health, which is what determines whether you can buy it at all.
Common mistakes with hospital indemnity insurance
Buying it as though it were health insurance. It pays cash on defined events. It does not cover medical bills in general and it is no substitute for a health plan.
Not matching the benefit days to the plan. A policy paying for ten days when your plan charges copays for five is paying for cover you will not use.
Assuming observation stays are covered. Many are not.
Stacking it on a Medigap plan. Usually redundant. Ask what gap remains.
Ignoring the pre-existing condition clause. It is the difference between a claim paid and a claim refused.
Medicare reference charts
The charts below cover the ground most questions start from.
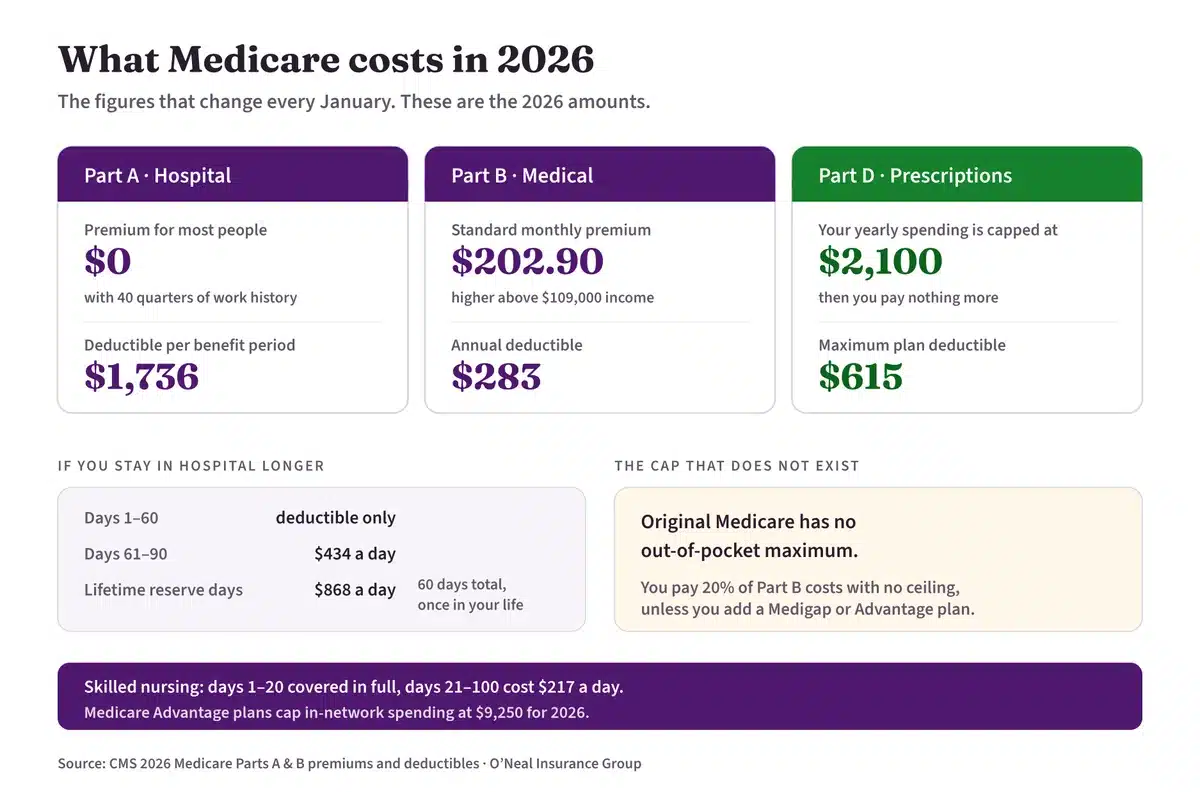
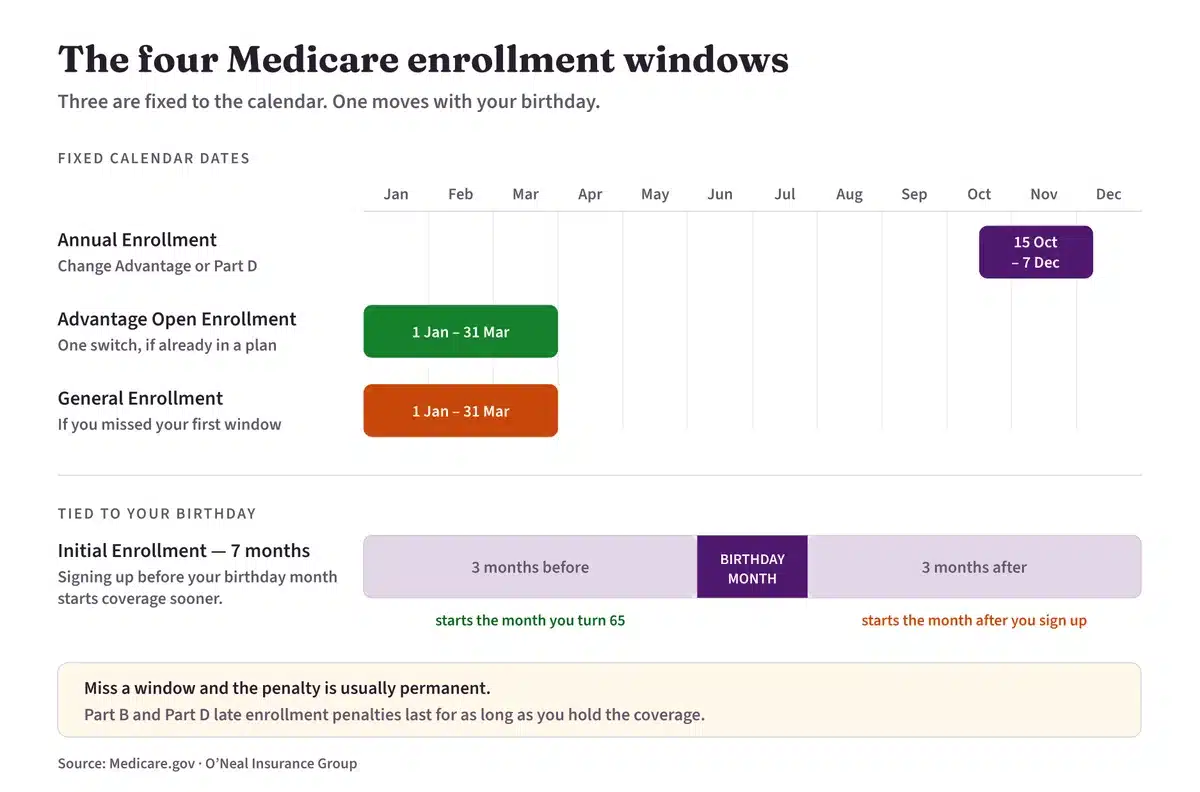
Check any of this independently
- Medicare.gov — inpatient hospital care — what Part A covers and what you pay
- Medicare.gov — Medicare costs — current deductibles and coinsurance
- SHIP National Technical Assistance Center — free counseling in your state, from people who sell nothing
- NAIC consumer tools — agent license and complaint lookup
Related guides on this site
- What Medicare Advantage costs — the copays hospital indemnity insurance is designed to meet
- How Medigap works — the alternative route, and why it changes the answer
- Critical illness cover — a lump sum on diagnosis rather than a daily benefit
- Book a no-cost appointment
Or call (877) 808-2900. We will look at your plan’s actual copay schedule first and tell you whether hospital indemnity insurance is worth buying at all in your case.
Personal guidance · No additional fee